Psoriatic Arthritis: How It Differs from Regular Psoriasis

Psoriasis and psoriatic arthritis are related conditions that are often confused with one another. While both involve the immune system and can occur together, they affect different parts of the body and require distinct approaches to diagnosis and treatment. Understanding these differences is essential for proper management.

What Is Psoriasis?

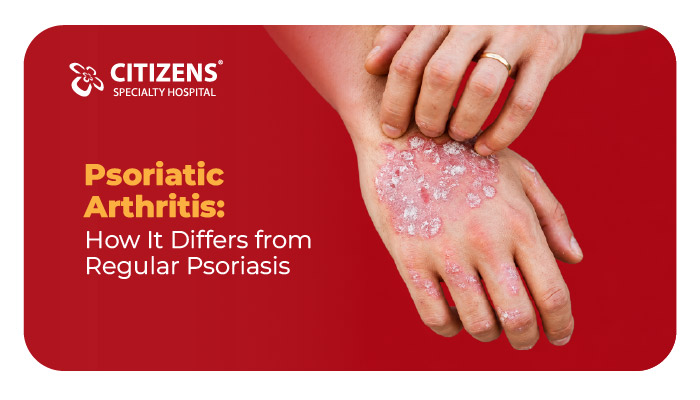
Psoriasis is a chronic autoimmune skin condition that causes skin cells to grow too quickly, resulting in thick, scaly patches called plaques. These patches commonly appear on the elbows, knees, scalp, and lower back, and can range from mild to severe in extent and severity.

What Is Psoriatic Arthritis?

Psoriatic arthritis (PsA) is a form of inflammatory arthritis that occurs in some people with psoriasis, though it can occasionally develop before skin symptoms appear. Unlike psoriasis, which primarily affects the skin, psoriatic arthritis involves inflammation of the joints, tendons, and entheses (where tendons and ligaments attach to bone).

Key Differences Between Psoriasis and Psoriatic Arthritis

  • Primary area affected – Psoriasis: Skin | Psoriatic Arthritis: Joints, tendons, and skin
  • Main symptoms – Psoriasis: Scaly plaques, itching | Psoriatic Arthritis: Joint pain, stiffness, swelling
  • Onset – Psoriasis: Any age, often before PsA | Psoriatic Arthritis: Usually years after skin symptoms, sometimes before
  • Diagnosis method – Psoriasis: Physical exam of skin | Psoriatic Arthritis: Physical exam, imaging, and blood tests
  • Long-term risk – Psoriasis: Skin-related complications | Psoriatic Arthritis: Potential joint damage and disability

Who Develops Psoriatic Arthritis?

Approximately 30% of people with psoriasis develop psoriatic arthritis at some point. Risk factors include:

  • Family history of psoriasis or psoriatic arthritis
  • Severity of skin psoriasis (though PsA can occur even with mild skin disease)
  • Nail psoriasis, which is strongly associated with joint involvement
  • Age, typically developing between 30 and 50 years old, though it can occur at any age

Symptoms of Psoriatic Arthritis

Joint Symptoms

  • Joint pain, swelling, and stiffness, often worse in the morning
  • Swelling of entire fingers or toes, giving a “sausage-like” appearance (dactylitis)
  • Pain and tenderness where tendons and ligaments attach to bones (enthesitis)
  • Reduced range of motion in affected joints
  • Symptoms can affect one side or both sides of the body, and joint involvement patterns vary widely

Additional Symptoms

  • Nail changes, including pitting, thickening, or separation from the nail bed
  • Eye inflammation (uveitis) in some cases
  • Fatigue
  • Lower back pain, if the spine is affected (psoriatic spondylitis)

How Is Psoriatic Arthritis Diagnosed?

  • Clinical evaluation – Assessing joint symptoms alongside any history or presence of psoriasis
  • Imaging – X-rays, ultrasound, or MRI to detect joint damage or inflammation
  • Blood tests – To rule out other types of arthritis, such as rheumatoid arthritis, since there’s no single definitive blood test for PsA
  • Nail and skin examination – Looking for characteristic changes that support the diagnosis

Diagnosis can sometimes be challenging, particularly when joint symptoms appear before skin changes, requiring a thorough evaluation by a rheumatologist.

Types of Psoriatic Arthritis

  • Asymmetric oligoarticular – Affects a few joints, often on one side of the body
  • Symmetric polyarticular – Affects multiple joints on both sides, resembling rheumatoid arthritis
  • Distal interphalangeal predominant – Primarily affects joints closest to the nails
  • Spondylitis – Primarily affects the spine and sacroiliac joints
  • Arthritis mutilans – A rare, severe form causing significant joint damage and deformity

Treatment Approaches

Treating Psoriasis (Skin)

  • Topical treatments, including corticosteroids and vitamin D analogs
  • Phototherapy (controlled UV light exposure)
  • Systemic medications for moderate to severe cases

Treating Psoriatic Arthritis (Joints)

  • NSAIDs – For mild joint pain and inflammation
  • Disease-modifying antirheumatic drugs (DMARDs) – To slow disease progression and prevent joint damage
  • Biologic therapies – Target specific parts of the immune system involved in inflammation
  • Targeted synthetic DMARDs – Newer oral medications targeting specific inflammatory pathways
  • Physical therapy – To maintain joint function and flexibility

Many modern treatments effectively address both skin and joint symptoms simultaneously, as they target the underlying immune dysfunction common to both conditions.

Living with Psoriatic Arthritis

  • Maintain regular follow-up with a rheumatologist to monitor disease activity and adjust treatment as needed
  • Engage in low-impact exercise to maintain joint mobility and overall health
  • Manage stress, which can trigger flares in both skin and joint symptoms
  • Maintain a healthy weight to reduce stress on joints
  • Consider working with a dermatologist and rheumatologist together for coordinated care

Complications if Left Untreated

  • Progressive joint damage and deformity
  • Reduced quality of life due to chronic pain and disability
  • Increased risk of cardiovascular disease, associated with chronic inflammation
  • Eye complications, such as uveitis

When to See a Doctor

If you have psoriasis and develop joint pain, swelling, or stiffness—especially if it persists for more than a few weeks, consult your doctor promptly. Early diagnosis and treatment of psoriatic arthritis can significantly reduce the risk of permanent joint damage.

Conclusion

While psoriasis and psoriatic arthritis are closely related, they affect different parts of the body and require distinct diagnostic and treatment approaches. Understanding these differences empowers patients to seek timely evaluation for joint symptoms, potentially preventing long-term joint damage. With modern treatment options, most people with psoriatic arthritis can effectively manage their symptoms and maintain an active lifestyle.

Frequently Asked Questions

Q: Can you have psoriatic arthritis without having psoriasis? A: Yes, in a small percentage of cases, joint symptoms can appear before skin symptoms, making diagnosis more challenging.

Q: Is psoriatic arthritis the same as rheumatoid arthritis? A: No, though they share some similarities, psoriatic arthritis is associated with psoriasis and often involves different joint patterns, including the spine and entheses.

Q: Can psoriatic arthritis be cured? A: There is currently no cure, but modern treatments can effectively control symptoms, slow disease progression, and help patients maintain a good quality of life.

Q: Does treating psoriasis prevent psoriatic arthritis? A: Not entirely, though effectively managing inflammation with certain systemic treatments may reduce the risk in some individuals.

Q: Can psoriatic arthritis affect the spine? A: Yes, a subtype called psoriatic spondylitis specifically affects the spine and sacroiliac joints, causing back pain and stiffness.